Gastrointestinal Endoscopy Market Analysis 2026-2031
- Single User License (1 Users) $ 3,500
- Team License (2~5 Users) $ 4,500
- Corporate License (>5 Users) $ 5,500
The global gastrointestinal (GI) endoscopy market size will reach between 16.5 to 19.5 billion USD in 2026, and the global GI endoscopy market is projected to expand at a compound annual growth rate (CAGR) of 5.2% to 7.2% through 2031. The GI endoscopy market is driven by four structural tailwinds: escalating epidemiological prevalence of colorectal cancer (CRC) and gastric malignancies; clinical migration from radical visceral surgery to organ-preserving submucosal interventions (EMR, ESD, POEM); stringent infection control mandates addressing cross-contamination in reusable endoscopes with complex elevator mechanisms; and health economics increasingly prioritizing zero-capital-expenditure, high-throughput diagnostic tools. North America currently commands the largest revenue share, driven by outpatient migration toward Ambulatory Surgical Centers (ASCs) and progressive reimbursement structures. Asia-Pacific represents the highest-velocity growth theatre, catalyzed by state-backed centralized procurement policies in China, high baseline gastric cancer incidence across East Asia, and expansive clinical modernization programs across India and Southeast Asia.
TAXONOMY AND TECHNOLOGICAL ARCHITECTURE
Gastrointestinal endoscopy systems comprise specialized intraluminal medical devices engineered to traverse natural digestive conduits. A complete operational endoscopy platform incorporates five technical sub-elements: a flexible mechanical insertion tube or wireless ingestible capsule, an illumination source (multispectral solid-state LED or laser diode array), an optical imaging assembly (distal-tip complementary metal-oxide-semiconductor [CMOS] or charge-coupled device [CCD] sensor paired with micro-lenses), a transmission architecture (micro-coaxial cabling, human body communication [HBC], or radiofrequency transceivers), and an image signal processor (ISP) mainframe executing real-time color matrix transformation, noise filtering, and edge contrast optimization.
A. Categorization by Clinical Function and Anatomic Target
● Upper Gastrointestinal (Upper GI) Endoscopes:
1. Gastroscopes: Oral-insertion flexible endoscopes engineered to visualize mucosal morphology across the esophagus, gastric cavity, and duodenal loop. Modern high-tier gastroscopes deploy multi-stage optical magnification (reaching up to 135x optical zoom), auxiliary water-jet delivery channels to clear mucosal debris, and multi-band spectral chromoendoscopy to identify early dysplasia, atrophic gastritis, and esophageal varices.
2. Duodenoscopes: Side-viewing, specialized flexible scopes dedicated to Endoscopic Retrograde Cholangiopancreatography (ERCP). These devices incorporate a distal mechanical Albarran elevator mechanism that manipulates cannulas, papillotomes, and guide wires into the Ampulla of Vater. Because the narrow crevices of the elevator channel severely impede reprocessing brush access, reusable duodenoscopes represent the highest microbial cross-contamination vector in interventional endoscopy.
● Lower Gastrointestinal (Lower GI) Endoscopes:
1. Colonoscopes: Extended-length flexible platforms (ranging from 130 cm to 170 cm) optimized for navigating the tortuous colonic lumen up to the cecum and terminal ileum. Contemporary colonoscopes feature variable-stiffness insertion tubes, dynamic deflection responsiveness, and ultra-wide fields of view (exceeding 170 degrees) to optimize adenoma detection rates (ADR) during primary colorectal cancer screening.
● Small Bowel Endoscopes:
1. Enteroscopes: Elongated, high-torque flexible scopes utilizing motorized, push, or balloon-assisted advancement systems (single-balloon or double-balloon enteroscopy) designed to access the deep jejunum and ileum. While balloon enteroscopy permits therapeutic tissue intervention, its extreme technical difficulty and extended procedure times have shifted diagnostic evaluation largely toward capsule modalities.
● Endoscopic Ultrasound (EUS) Platforms:
1. Echoendoscopes: Advanced hybrid diagnostic instruments housing high-frequency piezoelectric ultrasound transducers (radial 360-degree or curved linear array operating from 5 MHz to 12 MHz) positioned at the distal tip immediately adjacent to the optical lens. EUS platforms enable cross-sectional acoustic visualization through the mucosal wall, facilitating transmural staging of submucosal lesions, cystic neoplasms, and surrounding extra-luminal structures (mediastinal nodes, pancreas, biliary tree), alongside real-time ultrasound-guided Fine Needle Aspiration and Biopsy (FNA/FNB).
● Capsule Endoscopy Systems:
1. Axial (End-View) Systems: First- and second-generation ingestible capsules deploying a single or dual forward-facing optical sensor. These devices record images in a linear tunnel projection, frequently missing pathology obscured behind acute mucosal folds, and depend on external radiofrequency sensor belts and battery-powered recording packs tethered to the patient.
2. Panoramic (Lateral 360-Degree) Systems: Architectures integrating multiple laterally aligned CMOS image sensors positioned perpendicular to the capsule axis (e.g., CapsoCam Plus). This layout generates an unbroken 360-degree radial panoramic visualization of the luminal circumference. Onboard high-density flash memory replaces radiofrequency data transmission, eliminating external wearable receiver equipment and facilitating direct-to-cloud analytical workflows.
3. Magnetically Controlled Capsule Endoscopy (MCCE): Systems integrating internal magnetic components responsive to external multi-axis robotic magnetic fields. This enables the operator to actively guide capsule translation, levitation, and rotation within fluid-distended gastric cavities, delivering complete, unsedated mucosal surveys of the stomach.
B. Categorization by Lifecycle and Operational Paradigm
● Reusable Flexible Endoscopy Systems:
Durable, high-precision assemblies engineered from medical-grade fluoro-polymers, high-tensile stainless steel control cables, and micro-optical stacks. These platforms interface with centralized processing mainframes (such as the Olympus EVIS X1, Shanghai Aohua AQ-300, and SonoScape HD-550). While offering superior durability and uncompromised optical resolution, they impose substantial initial capital outlays, recurring annual maintenance overhead, and strict multi-stage high-level disinfection (HLD) or liquid chemical sterilization regimens that require up to 45 minutes per cycle.
● Single-Use and Disposable GI Endoscopy Solutions:
Sterile, patient-dedicated devices manufactured from optical-grade engineered thermoplastics and sub-millimeter CMOS assemblies that bypass hospital reprocessing suites entirely.
- Single-Use Scopes: Sterile single-use duodenoscopes (e.g., Boston Scientific EXALT Model D), disposable cholangioscopes (SpyGlass DS), and emerging single-use colonoscopes and gastroscopes engineered to eliminate hospital-acquired multi-drug resistant pathogens, minimize room turnover intervals, and mitigate capital expenditures.
- Ingestible Diagnostic Capsules: Single-use swallowable visualization capsules designed for single-patient diagnostic journeys through the small intestine, colon, or upper digestive tract, naturally evacuated without post-procedure retrieval or reprocessing infrastructure.
DOWNSTREAM CLINICAL APPLICATIONS AND VALUE MIGRATION
● Colorectal Cancer (CRC) and Gastric Cancer Screening
Colorectal cancer remains the second leading cause of cancer-related mortality globally. Optical colonoscopy, paired with simultaneous polypectomy and tissue biopsy, stands as the unequivocal diagnostic and preventative gold standard. The clinical performance of screening platforms is benchmarked directly against the Adenoma Detection Rate (ADR); clinical studies demonstrate that every 1.0% increase in ADR yields a 3.0% reduction in interval colorectal cancer incidence and a 5.0% decline in cancer mortality.
Concurrently, non-invasive screening modalities are addressing fundamental barriers in primary colonoscopy. Incomplete optical colonoscopies occur in 4% to 25% of clinical encounters due to redundant colonic loops, severe diverticular disease, pelvic adhesions, or patient intolerance to moderate sedation. In this cohort, colon capsule endoscopy provides a clinically validated diagnostic alternative. Clinical trials reveal that panoramic and dual-camera colon capsules demonstrate a 61.5% higher diagnostic yield for polyps larger than 5 mm relative to CT Colonography (CTC), alongside substantially higher detection sensitivity for polyps 6 mm or greater (78.2% versus 26.8%). In East Asian geographies, routine upper GI endoscopy constitutes the cornerstone of public health programs aiming to detect early gastric cancer (EGC), where superficial neoplastic lesions confined to the mucosal layer offer five-year survival rates exceeding 90%.
● Advanced Endoscopic Resection and Mucosal Interventions
The clinical treatment paradigm for early gastrointestinal neoplasms, high-grade dysplasias, and submucosal tumors has pivoted decisively away from high-morbidity surgical resections toward endoluminal organ-preserving therapeutics:
- Endoscopic Mucosal Resection (EMR): Involves submucosal fluid injection to elevate the targeted lesion away from the muscularis propria, followed by electrocautery snare transection. EMR is primarily utilized for sessile polyps and superficial lesions smaller than 20 mm.
- Endoscopic Submucosal Dissection (ESD): A micro-surgical endoluminal technique utilizing specialized electrosurgical knives to systematically dissect the submucosal connective tissue plane beneath early carcinomas. ESD enables en bloc, R0 margin-negative resections of large, irregular, or ulcerated neoplasms, significantly mitigating local recurrence rates irrespective of lesion size.
- Emerging Submucosal and Full-Thickness Techniques: Advanced endoluminal procedures including Peroral Endoscopic Myotomy (POEM) for esophageal achalasia, Submucosal Tunnel Endoscopic Resection (STER) for stromal tumors, and Endoscopic Full-Thickness Resection (EFR) utilizing specialized full-thickness clipping devices.
These complex procedures have transformed flexible endoscopy from a diagnostic capital equipment market into a high-margin, recurring consumable market. Therapeutic protocols consume extensive suites of specialized instrumentation: needle knives, insulated-tip knives, fine-focus electrocautery snares, specialized submucosal injection lifting agents, 360-degree rotatable hemostatic clips, and endoscopic suturing devices.
● Pancreaticobiliary Diagnostics and Interventions
Disorders of the biliary tree and pancreas—including choledocholithiasis, benign and malignant biliary strictures, pancreatic pseudocysts, and adenocarcinoma—demand high-precision interventional guidance:
- Endoscopic Retrograde Cholangiopancreatography (ERCP): Combines fluoroscopy with optical visualization to cannulate the common bile duct and pancreatic duct, executing sphincterotomies, mechanical lithotripsy, and stent deployments.
- Single-Use Digital Cholangioscopy: Direct endoluminal visualization of the biliary ductal mucosa via ultra-slim single-use catheter scopes. By delivering direct 4K/HD digital imaging within sub-centimeter bile ducts, systems like SpyGlass eliminate the ambiguous filling defects characteristic of standard 2D fluoroscopy, guiding electrohydraulic or laser lithotripsy and enabling targeted micro-biopsies.
- Interventional Biliary Drainage: Utilization of fully covered self-expanding metal stents (SEMS) and specialized lumen-apposing metal stents (LAMS) deployed under EUS guidance to drain walled-off pancreatic necrosis and construct endoscopic gastrojejunostomies.
- Early Pancreatic Neoplasia Screening: Advanced panoramic capsule endoscopy platforms have demonstrated an 82% visualization rate of the duodenal papilla (Ampulla of Vater), starkly contrasting with the 10% to 15% identification rates recorded by legacy forward-facing axial capsule scopes. This technical capability establishes a non-invasive screening corridor to detect papillary enlargement and early-stage periampullary carcinomas prior to obstructive jaundice onset.
● Small Bowel Pathology and Obscure GI Bleeding (OGIB)
Obscure gastrointestinal bleeding—defined as persistent or recurrent bleeding from the GI tract without an identified etiology following negative standard upper gastroscopy and lower colonoscopy—accounts for roughly 5% of all clinical gastrointestinal hemorrhage presentations. Approximately 80% of these bleeding events stem from pathologies localized in the 20-foot expanse of the small bowel, such as vascular angioectasias, neuroendocrine tumors, Crohn's disease ulcerations, and NSAID-induced enteropathy.
Wireless capsule endoscopy is universally established as the first-line diagnostic standard for OGIB evaluation, exhibiting diagnostic yields ranging from 30% to 70%, which significantly exceeds push enteroscopy (roughly 31%) and double-balloon enteroscopy (roughly 23%). Field intelligence indicates that the global small bowel capsule endoscopy market is projected to reach approximately 335 million USD by 2030, with the North American market absorbing roughly 126 million USD of this total.
SUPPLY CHAIN AND VALUE CHAIN ARCHITECTURE
● Upstream Tier-2/Tier-3: Core Optoelectronic Components and Specialized Materials
The performance ceilings of gastrointestinal endoscopy platforms are fundamentally determined by upstream component suppliers specializing in sub-millimeter optoelectronics and biocompatible polymer chemistry:
- CMOS Image Sensors: The migration from legacy CCD arrays to distal-tip ultra-compact CMOS sensors has enabled HD and 4K visualization within narrow working channels. The global supply is anchored by a narrow tier of advanced semiconductor fabricators, notably Toshiba Corporation and Canon Inc. in Japan, AMS OSRAM in Europe, and OmniVision in the United States and China. CapsoVision, for example, has sustained an exclusive image sensor manufacturing relationship with Toshiba spanning over 11 years.
- Precision Micro-Lens Assemblies: Custom micro-optical glass and resin lens stacks engineered to withstand continuous liquid immersion and provide precise focal depths from 2 mm to 100 mm. Taiwan, China serves as the dominant global epicenter for precision miniature optics fabrication, anchored by firms such as Largan Precision Co., Ltd., which has operated as a foundational single-source micro-lens supplier to capsule endoscopy developers for nearly two decades.
- Application-Specific Integrated Circuits (ASICs) and Embedded FPGAs: Micro-chipsets designed into multi-chip packages (MCP) executing automated white balance, high-efficiency video compression (H.265/HEVC), high dynamic range tone mapping, and micro-power management without generating excessive thermal dissipation at the distal scope tip. Core design and manufacturing partners include Moai Electronics Corporation and Speedbridge Technology Co. in Taiwan, China.
- Biocompatible Raw Materials: Advanced extrusion polymers, including thermoplastic polyurethanes (TPU), polytetrafluoroethylene (PTFE) low-friction channel liners, medical-grade silicones, biocompatible structural adhesives, and micro-coaxial braided wiring assemblies designed to resist enzymatic degradation and harsh reprocessing chemicals.
● Midstream Tier-1: System Integration, Algorithm Development, and Sterile Manufacturing
Midstream system manufacturers synthesize upstream optoelectronics into clinically deployable platforms, managing core engineering competencies:
- Sub-Millimeter Optomechanical Alignment: Automated robotic alignment of micro-lens barrels over active CMOS pixel arrays to eliminate optical tilt and decentering, ensuring uniform edge-to-edge optical resolution.
- Image Signal Processor (ISP) and Algorithmic Chromoendoscopy: Creation of proprietary image processing pipelines running on field-programmable gate arrays or customized system-on-chip (SoC) architectures. These engines power multi-spectral optical chromoendoscopy (e.g., Olympus NBI, Fujifilm BLI/LCI, Aohua CBI, SonoScape SFI) by isolating narrow blue and green absorption bands that match the hemoglobin absorption spectrum, accentuating microvascular topography without manual chemical dye spray.
- Custom Sensor and Micro-Camera Architecture: Transitioning from standardized commercial consumer sensors to proprietary 1:1 square aspect-ratio CMOS sensor designs. Projects such as Zhuhai Pusen's custom Rose Module demonstrate this evolution, aligning sensor active areas directly with round gastrointestinal working channels to eliminate wasted peripheral pixels and compress bill-of-materials (BOM) overhead.
- Cleanroom Scale and Automated Production: High-throughput Class 100,000 cleanroom facilities engineered for high-yield automated micro-soldering, adhesive dispensing, and automated leak-integrity testing, fulfilling ISO 13485 certification and automated terminal ethylene oxide (EtO) sterilization standards.
● Downstream: Clinical Facilities and Reimbursement Realities
The downstream segment encompasses clinical delivery environments alongside the healthcare payers underwriting procedure costs:
- Tertiary Academic Medical Centers: High-capacity clinical institutes conducting complex diagnostic and organ-preserving therapeutic interventions (ESD, POEM, double-balloon enteroscopy, ERCP, EUS-FNA). These institutions prioritize top-tier 4K/3D reusable capital towers, EUS systems, and extensive inventories of premium electrosurgical consumables.
- Secondary and Municipal Hospitals: Regional facilities executing routine screening, surveillance gastroscopy, and diagnostic colonoscopy. This segment is characterized by heightened price sensitivity, driving the adoption of cost-effective platforms from emerging Asian manufacturers.
- Ambulatory Surgical Centers (ASCs) and Specialty Endoscopy Suites: Rapidly expanding outpatient procedural environments in North America and Western Europe focused on cost-per-procedure optimization, rapid suite turnover, and high throughput. ASCs are the primary adoption engine for single-use scopes and zero-capital-expenditure panoramic capsule workflows that circumvent centralized sterile reprocessing bottlenecks.
- Payers and Reimbursement Architecture: Reimbursement is dictated by national single-payer rate cards or private commercial fee schedules governed by Current Procedural Terminology (CPT) and Diagnosis-Related Group (DRG) structures. Capital outlays and disposable instrument adoption hinge directly on specific billing mechanisms; for example, novel out-of-hospital capsule applications and high-risk single-use scopes depend heavily on the establishment of adequate facility fees and dedicated pass-through reimbursement codes.
REGIONAL MARKET DYNAMICS AND POLICY FRAMEWORKS
● North America
North America maintains its position as the largest regional market.
- Regulatory Landscape: The U.S. Food and Drug Administration (FDA) stringently governs flexible and capsule endoscopy devices via 510(k) premarket notifications, De Novo classifications, and Premarket Approvals (PMA). Persistent FDA safety alerts regarding fatal Carbapenem-Resistant Enterobacteriaceae (CRE) superbug outbreaks linked to the elevator mechanisms of reusable duodenoscopes have actively driven clinical protocols toward single-use duodenoscopes and scopes featuring disposable sterile endcaps. In December 2024, the FDA granted expanded clearance for remote ingestion and telemedicine administration of CapsoCam Plus, enabling fully decentralized, at-home capsule endoscopy. The FDA also bifurcates the regulatory evaluation of AI software modules (CADe/CADx) from endoscopic hardware, requiring dedicated comparative diagnostic clinical trials utilizing established algorithmic predicates (such as the NaviCam ProScan clearance pathway). In parallel, the FDA Breakthrough Device Designation pathway is being leveraged by innovators targeting early-stage pancreatic cancer visualization via the Ampulla of Vater.
- Reimbursement Architecture: The Centers for Medicare and Medicaid Services (CMS) shapes provider economics via the Inpatient Prospective Payment System (IPPS) using MS-DRGs and the Outpatient Prospective Payment System (OPPS). The Calendar Year 2026 Medicare Physician Fee Schedule (PFS) Final Rule established stabilized reimbursement rates for capsule and flexible procedures within non-hospital private office settings. CPT codes establish uniform reimbursement for small bowel and colon capsule studies. Market operations are further governed by Physician Payments Sunshine Act transparency reporting, while import supply lines navigate national security trade reviews, including Department of Commerce Section 232 investigations into critical medical equipment dependency. The continuous migration of diagnostic screening colonoscopies into ASCs drives rapid demand for single-use consumables that eliminate capital processing depreciation.
● Asia-Pacific
Asia-Pacific represents the highest-velocity expansion theatre, anchored by high regional cancer prevalence and extensive healthcare modernizations.
- China: The National Medical Products Administration (NMPA) enforces rigorous clinical evaluation and type-testing protocols. The central government's Volume-Based Procurement (VBP) programs aggregate public hospital demand to enforce sweeping unit price reductions, often compressing supplier prices by 50% to 75% on standard therapeutic accessories and flexible capital towers. Simultaneously, state-level "Buy Chinese" industrial policies actively prioritize domestic manufacturers—such as Shanghai Aohua, SonoScape Medical, Zhuhai Pusen, and NovelBeam—over multinational suppliers in regional and national hospital procurement tenders.
- Japan: Regulated by the Pharmaceuticals and Medical Devices Agency (PMDA), Japan features the highest per-capita utilization of upper GI endoscopy globally. The universal standard-of-care status of ESD for early gastric cancer fosters an advanced domestic market for micro-precision resection consumables (e.g., Olympus DualKnife, Finemedix ClearCut).
- South Korea: Governed by the Ministry of Food and Drug Safety (MFDS) and funded via the single-payer National Health Insurance (NHI) service, South Korea serves as an innovation crucible for articulate robotic instruments (such as LivsMed ArtiSential) and ingestible technologies. Domestic capital restructuring has recently driven capsule pioneers like IntroMedic to navigate the K-OTC market to recapitalize core optical production lines.
- India and Southeast Asia: Emerging tertiary healthcare chains across India, Indonesia, and Vietnam are accelerating equipment procurement, driven by the expansion of private healthcare insurance and the development of metropolitan endoscopy centers of excellence.
● Europe
Europe stands as the second-largest regional market, led by Germany, the United Kingdom, France, Italy, and Spain.
- Regulatory Landscape: The transition to the European Union Medical Device Regulation (EU MDR 2017/745) has fundamentally transformed the commercialization timeline. EU MDR demands extensive post-market clinical follow-up (PMCF), comprehensive Unique Device Identification (UDI) implementation, and unannounced Notified Body production audits. Although legislative revisions pushed compliance deadlines to December 2027 for high-risk Class III devices and December 2028 for Class IIa/IIb systems, the severe capacity constraints across designated Notified Bodies have dramatically inflated certification costs, inducing multinational manufacturers to rationalize low-volume legacy portfolios and prioritize initial product introductions within the United States.
- Policy and Sustainability: Healthcare delivery is directed by national single-payer structures (e.g., the NHS in the UK, G-BA in Germany, HAS in France) utilizing formal Health Technology Assessments (HTA) that demand rigorous cost-effectiveness data. Financial headwinds are reinforced by statutory regional cost-containment measures, most notably the Italian Payback Law, which mandates that medical technology vendors retroactively reimburse regional governments for aggregate healthcare budget overages. Furthermore, Europe leads the global market in environmental, social, and governance (ESG) healthcare mandates, compelling single-use manufacturers to establish formal closed-loop circular recycling frameworks (such as the Ambu Recircle Program) across Germany, France, and the UK to transform single-use plastics into post-consumer technical polymers.
● Latin America
Latin America is an emerging market with procedure volumes concentrated in Brazil, Mexico, Colombia, Argentina, and Chile.
- Operational Environment: Device approvals are overseen by national agencies, primarily ANVISA in Brazil, COFEPRIS in Mexico, and INVIMA in Colombia. The commercial environment is split between resource-constrained public hospital systems reliant on centralized tenders and expansive private healthcare networks catering to medical tourism and insured populations.
- Market Dynamics: Severe macroeconomic fluctuations and recurring local currency depreciations against the USD elevate import expenses for premium capital visualization systems. This economic friction has driven rapid adoption of high-performance, cost-effective reusable towers developed by Chinese OEMs, alongside an expanding market for contract endoscope repair services and third-party refurbished systems.
● Middle East and Africa (MEA)
The MEA territory represents a bifurcated market, displaying profound infrastructural contrasts across sub-regions.
- The Middle East: Anchored by the Gulf Cooperation Council (GCC) nations—primarily Saudi Arabia, the United Arab Emirates, and Qatar—alongside Israel. Procurement is managed centrally by organizations such as the Gulf Health Council (GHC) and governed by modern health authorities including the Saudi Food and Drug Authority (SFDA). Driven by massive public healthcare investments, GCC nations feature rapid capital deployment, state-of-the-art academic medical cities, and rapid adoption of high-definition 4K towers, EUS systems, and robotic capsule platforms.
- Africa: Markets across Sub-Saharan Africa and North Africa (including South Africa, Egypt, Nigeria, and Kenya) remain highly price-sensitive, with procurement driven by international healthcare aid organizations, development bank grants, and targeted public health tenders. Clinical demand centers almost entirely on highly durable, mechanically robust flexible gastroscopes and colonoscopes requiring minimal technical maintenance and capable of surviving manual disinfection workflows.
COMPETITIVE DOSSIERS
● Olympus Corporation: Olympus commands approximately 65% to 70% of the global flexible gastrointestinal endoscopy market. Its primary competitive moat is built upon an entrenched installed base across academic medical centers and tertiary hospitals, extensive global service and repair networks, and deeply established clinical workflows.
● HOYA Corporation (PENTAX Medical): HOYA’s PENTAX Medical division occupies a resilient Tier-1 market position, differentiated by robust mechanical build quality, open architectural integration, and advanced computational chromoendoscopy algorithms.
● Fujifilm: Fujifilm leverages decades of photographic optical science, solid-state LED illumination engineering, and high-performance image sensor fabrication.
● The rest of companies covered in the report: Shanghai Aohua Photoelectricity Endoscope Co. Ltd., SonoScape Medical Corp., Medtronic, CapsoVision, Inc., IntroMedic Co., Ltd., Jinshan Science & Technology (Group), AnX Robotics, Insight Medical Solutions Inc. (IMS), Richard Wolf GmbH, and Beijing Huagen Anbang Technology Co. Ltd.
STRUCTURAL OPPORTUNITIES AND SYSTEMIC BOTTLENECKS
● Opportunities
1. Algorithmic Chromoendoscopy and Edge AI (CADe/CADx):
The clinical integration of deep learning neural networks represents the most significant software-driven expansion within flexible endoscopy. Real-time CADe algorithms mitigate operator fatigue and experience variance by establishing automated bounding boxes around missed diminutive or flat lesions, directly elevating the Adenoma Detection Rate (ADR). Concurrently, computer-aided characterization (CADx) algorithms deploy real-time microvascular pattern analysis to predict polyp histology (differentiating non-neoplastic hyperplastic lesions from pre-cancerous adenomas). This capability operationalizes the "diagnose-and-leave-behind" and "resect-and-discard" clinical paradigms, potentially saving healthcare payers hundreds of millions of dollars annually in unnecessary pathology laboratory processing fees.
2. Outpatient Migration to Ambulatory Surgical Centers (ASCs) and Home Telemedicine:
In mature healthcare economies, procedures are steadily migrating away from tertiary hospital suites toward ASCs and private outpatient facilities. In the United States, this transition is incentivized by favorable ambulatory facility fee schedules and private payer mandates. ASCs operate on lean staffing models and demand rapid suite turnover times. Consequently, technologies that eliminate centralized reprocessing infrastructure—specifically zero-capital-cost panoramic capsule systems and single-use scopes—are positioned for rapid adoption. Furthermore, the FDA's regulatory clearance of at-home ingestion protocols for CapsoCam Plus provides a foundation for fully decentralized gastrointestinal surveillance, decoupling endoscopy throughput from clinical physical real estate constraints.
3. Expansion of Recurring Interventional Consumable Revenue:
While capital equipment procurement operates on cyclical five- to seven-year replacement budgets, therapeutic consumables generate high-margin recurring cash flows. The universal adoption of advanced submucosal interventions (ESD, EMR, POEM, STER) for early gastric, esophageal, and colorectal neoplasms requires sophisticated instrument kits: micro-knives, rotatable hemostatic clips, endoscopic suturing tools, and specialized submucosal injection formulas. Manufacturers that deploy high-performance therapeutic consumables alongside open-architecture camera towers are creating durable, counter-cyclical recurring revenue streams.
● Systemic Bottlenecks and Structural Challenges
1. Regulatory Friction and Bifurcated Dual-Track Clearances:
The implementation of the EU Medical Device Regulation (EU MDR 2017/745) has inflated the cost and complexity of medical device commercialization. Extended clinical evaluation requirements and severe Notified Body backlogs have delayed new product rollouts across the European continent relative to North American timelines. Concurrently, in the United States, the FDA enforces a bifurcated regulatory framework that categorizes optical physical scope hardware and AI detection software under separate regulatory classifications. Securing clearances requires multi-arm prospective clinical trials using complex algorithmic predicates, creating substantial regulatory hurdles for integrated device-software platforms.
2. Price Compression Under Volume-Based Procurement and Payer Clawbacks:
Government-mandated price-containment programs represent a significant structural headwind for capital margins. China's Centralized Volume-Based Procurement (VBP) policy continues to enforce drastic price reductions across flexible endoscopes, laparoscopic optics, and interventional accessories, forcing foreign multinationals to slash distribution margins or risk exclusion from public hospital channels. Similarly, across Europe, national cost-containment frameworks—such as the Italian Payback Law, which mandates industry refunds when regional health authorities exceed budgetary ceilings—directly erode operating income.
3. Upstream Optoelectronic Concentration and Geopolitical Fragility:
The global gastrointestinal endoscopy manufacturing sector is dependent upon highly concentrated upstream sub-tier suppliers. Critical sub-millimeter CMOS image sensors are sourced from a narrow tier of fabricators across Japan and the United States, while custom micro-optical lens modules, ASICs, and flexible printed circuit boards remain heavily concentrated in Taiwan, China. Geopolitical instability across East Asian maritime trade corridors, alongside tightening export restrictions on precision optoelectronic technologies, poses systemic supply-chain continuity risks for midstream system integrators globally.
1.1 Study Framework and Analytical Horizon (2021-2031) 1
1.2 Multilateral Research Methodology and Primary Validation Engine 2
1.3 Secondary Data Filtration, Supply-Side Audits, and Macro Indicators 3
1.4 Bottom-Up and Top-Down Econometric Modeling 4
1.5 Definitional Boundaries, Exchange Rates, and Forecasting Assumptions 5
1.6 Standard Terminology and Industry Abbreviations Directory 6
Chapter 2 Global Gastrointestinal Endoscopy Industry Landscape and Value Chain Architecture 7
2.1 End-to-End Gastrointestinal Endoscopy Value Chain Decomposition 7
2.2 Upstream Precision Components, Optical Bundles, CMOS/CCD Image Sensors, and Micro-Mechanics 8
2.3 Midstream System Integration, Video Processors, Light Sources, and Articulation Dynamics 9
2.4 Cross-Contamination Risk Protocols, Reprocessing Infrastructure, and Cleaning Chemistries 10
2.5 Single-Use Disruption: Ergonomic, Sterility, and Cost-Per-Procedure Paradigm Shifts 11
2.6 Pricing Dynamics, Bill-of-Materials (BOM) Deconstruction, and Margin Distribution 12
2.7 Downstream Health Economics: Capital Expenditure (CapEx) vs. Operational Expenditure (OpEx) Procurement Models 13
Chapter 3 Global Gastrointestinal Endoscopy Trade Dynamics, Regulatory Regimes, and Supply Chain Vulnerabilities 14
3.1 International Trade Flows: Major Export Corridors (Japan, Germany, China) and Import Sinks 14
3.2 Supply Chain Nearshoring, Domestic Sourcing Directives, and Critical Component Bottlenecks 15
3.3 Global Regulatory Harmonization: US FDA 510(k)/PMA Pathways and MDR (EU) 2017/745 Shifts 16
3.4 China National Medical Products Administration (NMPA) Registration Dynamics and Volume-Based Procurement (VBP) 17
3.5 Post-Market Surveillance and Sterilization Standards for Duodenoscopes and Elevators 18
3.6 Geopolitical Realignment, Dual-Use Tech Constraints, and Tariff Exposure 19
Chapter 4 Global Gastrointestinal Endoscopy Market by Product Architecture and Lifecycle 20
4.1 Reusable Flexible Gastrointestinal Endoscopy Systems 20
4.1.1 Optical Resolution Scaling: 4K UHD, Multi-Spectrum Imaging, and Narrow-Band Chromoendoscopy 21
4.1.2 Capital Cost Depreciation, Automated Endoscope Reprocessor (AER) Infrastructure, and Total Cost of Ownership 22
4.1.3 Market Size and Volume Forecast (2021-2031) 23
4.2 Single-Use / Disposable Gastrointestinal Endoscopy Systems 24
4.2.1 Infection Prevention Economics, Zero-Reprocessing Overhead, and Clinical Niche Penetration 25
4.2.2 Micro-CMOS Sensor Miniaturization, Plastic Optical Fibers, and Cost-Efficiency Curves 26
4.2.3 Market Size and Volume Forecast (2021-2031) 27
Chapter 5 Global Gastrointestinal Endoscopy Market by Clinical Functionality and Optical Subsystem 28
5.1 Upper Gastrointestinal Endoscopes (Gastroscopes) 28
5.1.1 Diagnostic vs. Therapeutic Channels, High-Definition Zoom, and Transnasal Modalities 29
5.2 Lower Gastrointestinal Endoscopes (Colonoscopes) 30
5.2.1 Retroflexion Capabilities, Variable Stiffness Dynamics, and Wide-Angle Field of View 31
5.3 Duodenoscopes 32
5.3.1 Disposable Endcap Systems, Removable Elevator Mechanisms, and Single-Use Duodenoscope Commercialization 33
5.4 Small Bowel Endoscopes (Enteroscopes) 34
5.4.1 Spiral Enteroscopy, Single-Balloon, and Double-Balloon System Performance 34
5.5 Endoscopic Ultrasound (EUS) Systems 35
5.5.1 Radial vs. Curved Linear Array Transducers, Elastography, and Fine-Needle Aspiration/Biopsy Interventions 35
5.6 Capsule Endoscopy Systems 36
5.6.1 Ingestible Sensor Architecture, Magnetically Controlled Capsule Gastroscopy (MCCG), and Data Transmission 36
5.7 Segment Market Revenue and Procedural Volumes (2021-2031) 37
Chapter 6 Global Gastrointestinal Endoscopy Market by Downstream Indication and Clinical Application 38
6.1 Colorectal Cancer (CRC) and Gastric Cancer Screening 38
6.1.1 Population-Wide Screening Guidelines, Adenoma Detection Rates (ADR), and AI-Assisted Lesion Detection 39
6.2 Advanced Endoscopic Resection 40
6.2.1 Endoscopic Mucosal Resection (EMR) and Endoscopic Submucosal Dissection (ESD) Hardware Adoption 41
6.3 Pancreaticobiliary Diagnostics and Interventions 42
6.3.1 Endoscopic Retrograde Cholangiopancreatography (ERCP), Biliary Stenting, and Sphincterotomy 43
6.4 Small Bowel Pathology and Obscure Gastrointestinal Bleeding (OGIB) 44
6.4.1 Deep Enteroscopy Navigation and Capsule Endoscopy Diagnostic Yield 44
6.5 Cross-Application Comparative Growth Trajectories (2021-2031) 45
Chapter 7 North America Gastrointestinal Endoscopy Market Supply, Demand, and Competitive Posture 46
7.1 Macro Regional Overview: Procedural Volume Shifts to Ambulatory Surgical Centers (ASCs) 46
7.2 United States: Reimbursement Codes (CPT/CMS), Disposables Adoption, and Strategic Sourcing 47
7.2.1 Supply Base, Manufacturing Infrastructure, and High-Definition Installed Base 48
7.2.2 US Market Size by Architecture, Modality, and Indication (2021-2031) 49
7.3 Canada: Public Healthcare Tendering, Capital Procurement Cycles, and Reprocessing Standards 50
7.3.1 Canadian Market Size and Forecast (2021-2031) 51
Chapter 8 Europe Gastrointestinal Endoscopy Market Supply, Demand, and Structural Realignment 52
8.1 European Union Framework: MDR Transition, Centralized Tendering, and Cross-Border Sourcing 52
8.2 Germany: Precision Engineering Hub, In-Hospital Endoscopy Workflows, and DRG Tariff Structures 53
8.3 France: Public-Private Hospital Tenders and Single-Use Technology Penetration 54
8.4 United Kingdom: NHS Screening Backlog Liquidation, ASC Expansion, and Decarbonization Targets 55
8.5 Italy: Regional Healthcare Autonomy, Equipment Modernization Funds, and Utilization Rates 56
8.6 Rest of Europe Market 57
Chapter 9 Asia-Pacific Gastrointestinal Endoscopy Market: Primary Production Hubs and High-Growth Basins 58
9.1 Macro Regional Dynamics: Screening Deficits, Dual-Tier Healthcare Models, and Localization Demands 58
9.2 Japan: Global Precision Optics Manufacturing Epicenter, Advanced ESD Adoption, and Reimbursement 59
9.3 China: Domestic Manufacturing Acceleration, VBP Pressure, and County-Level Hospital Penetration 61
9.4 South Korea: High-Density Gastric Cancer Screening Infrastructure and Innovation Pipelines 62
9.5 India & Southeast Asia: Tertiary Care Expansion, Refurbished Market Dynamics, and Indigenous Assembly Trends 63
9.6 Taiwan (China): Medical Electronics Assembly, Diagnostic Micro-Optics, and Market Forecast (2021-2031) 64
Chapter 10 Latin America, Middle East, and Africa Gastrointestinal Endoscopy Market Landscape 65
10.1 Latin America Regional Infrastructure and Fiscal Realities 65
10.1.1 Brazil: SUS Procurement vs. Private Hospital Networks, Import Duties, and Market Forecast (2021-2031) 66
10.1.2 Mexico: IMSS Procurement Cycles, Nearshoring Synergies, and Market Forecast (2021-2031) 67
10.2 Middle East and Africa Strategic Nodes 67
10.2.1 GCC Economies: High-End Video Endoscopy Modernization and Premium Hospital Center Investments 68
10.2.2 South Africa: Tier-1 Private Networks vs. Resource-Constrained Public Tenders 69
Chapter 11 Global Competitive Benchmarking, Industry Consolidation, and Strategic Group Analysis 70
11.1 Global Tiered Market Structure: The Japanese Oligopoly vs. Disruptive Market Entrants 70
11.2 Market Concentration Metrics: Herfindahl-Hirschman Index (HHI) and C4/C8 Ratios (2021-2026) 71
11.3 Multi-Parameter Competitive Heatmap: Resolution, Form Factor, Service Footprint, and Cost Ratio 72
11.4 Strategic M&A, Direct Distribution Integration, and AI Co-Development Partnerships (2021-2026) 73
11.5 Patent Landscapes: Optical Coherence, Magnetic Capsule Steering, and Robotic Articulation 74
Chapter 12 Corporate Intelligence: Strategic Benchmarking and Financial Performance of Key Competitors 75
12.1 Olympus Corporation 75
12.1.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 75
12.1.2 SWOT Diagnostic Matrix 76
12.1.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 77
12.2 HOYA Corporation (PENTAX Medical) 78
12.2.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 78
12.2.2 SWOT Diagnostic Matrix 79
12.2.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 80
12.3 Fujifilm Holdings Corporation 81
12.3.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 81
12.3.2 SWOT Diagnostic Matrix 82
12.3.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 83
12.4 Medtronic plc 84
12.4.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 84
12.4.2 SWOT Diagnostic Matrix 85
12.4.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 86
12.5 Shanghai Aohua Photoelectricity Endoscope Co. Ltd. 87
12.5.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 87
12.5.2 SWOT Diagnostic Matrix 88
12.5.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 89
12.6 SonoScape Medical Corp. 90
12.6.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 90
12.6.2 SWOT Diagnostic Matrix 91
12.6.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 92
12.7 Richard Wolf GmbH 93
12.7.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 93
12.7.2 SWOT Diagnostic Matrix 94
12.7.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 95
12.8 IntroMedic Co., Ltd. 96
12.8.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 96
12.8.2 SWOT Diagnostic Matrix 97
12.8.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 98
12.9 CapsoVision, Inc. 99
12.9.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 99
12.9.2 SWOT Diagnostic Matrix 100
12.9.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 101
12.10 Chongqing Jinshan Science & Technology (Group) Co., Ltd. 102
12.10.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 102
12.10.2 SWOT Diagnostic Matrix 103
12.10.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 104
12.11 AnX Robotics Inc. 105
12.11.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 105
12.11.2 SWOT Diagnostic Matrix 106
12.11.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 107
12.12 Insight Medical Solutions Inc. 108
12.12.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 108
12.12.2 SWOT Diagnostic Matrix 109
12.12.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 110
12.13 Beijing Huagen Anbang Technology Co., Ltd. 111
12.13.1 Corporate Structure, Optical Footprint, and Product Portfolio Overview 111
12.13.2 SWOT Diagnostic Matrix 112
12.13.3 Gastrointestinal Endoscopy Revenue, Cost of Goods Sold, Gross Margin, and Global Market Share (2021-2026) 113
Chapter 13 Global Gastrointestinal Endoscopy Strategic Synthesis and Future Trajectory (2027-2031) 114
13.1 Cross-Currents: Reusable Durability vs. Single-Use Expansion Frontiers 114
13.2 Next-Generation Paradigms: Autonomous Navigation, Microrobotics, and AI Augmented Biopsy 115
13.3 Consolidated Industry Forecasts and Strategic Action Vectors to 2031 116
Table 2 Gastrointestinal Endoscopy Standard Nomenclature and Technical Abbreviations 6
Table 3 Upstream Component Sourcing Matrix: Optoelectronic Sensors, Illumination, and Sheathing Polymers 8
Table 4 Reprocessing Lifecycle Cost Analysis: Standard Flexible Scope vs. AER Chemistries vs. Sterilization Cycles 10
Table 5 Single-Use vs. Reusable Flexible Endoscope Cost-Per-Procedure Amortization Model 12
Table 6 Global Gastrointestinal Endoscopy Cross-Border Flow and Export Value by Origin Country (2021-2026) 14
Table 7 Regulatory Clearances and Elevating Mechanism Sanitization Mandates (FDA, MDR, NMPA) 16
Table 8 Global Gastrointestinal Endoscopy Market by Lifecycle Modality: Revenue and Growth (2021-2031) 20
Table 9 Global Reusable Flexible GI Endoscope Market by Subsystem Component (2021-2031) 23
Table 10 Global Disposable/Single-Use GI Endoscope Market by Clinical Indication (2021-2031) 27
Table 11 Global Gastrointestinal Endoscopy Market by Clinical Function: Revenue (2021-2031) 28
Table 12 Global Gastroscope Shipments, Average Selling Prices, and Revenue (2021-2031) 30
Table 13 Global Colonoscope Shipments, Replacement Rates, and Revenue (2021-2031) 32
Table 14 Global Duodenoscope Revenue by Design Architecture: Reusable vs. Single-Use Elevator/Scope (2021-2031) 33
Table 15 Global Enteroscope and EUS System Shipments and Revenue (2021-2031) 35
Table 16 Global Capsule Endoscopy Shipments, Active Patient Kits, and Revenue (2021-2031) 37
Table 17 Global Gastrointestinal Endoscopy Market by Downstream Indication (2021-2031) 38
Table 18 Colorectal and Gastric Cancer Screening Endoscopy Procedure Volume and Revenue (2021-2031) 40
Table 19 Advanced Endoscopic Resection (EMR/ESD) Instrument and Scope Market Size (2021-2031) 41
Table 20 Pancreaticobiliary Intervention (ERCP/EUS-FNA) Hardware Market Size (2021-2031) 43
Table 21 Small Bowel Pathology and OGIB Endoscopy Market Size (2021-2031) 45
Table 22 North America Gastrointestinal Endoscopy Market by Lifecycle and Function (2021-2031) 46
Table 23 United States Gastrointestinal Endoscopy Revenue by Product Sub-Segment (2021-2031) 49
Table 24 Canada Gastrointestinal Endoscopy Revenue by Product Sub-Segment (2021-2031) 51
Table 25 Europe Gastrointestinal Endoscopy Market by Country/Region (2021-2031) 52
Table 26 Germany Gastrointestinal Endoscopy Revenue by Product Architecture (2021-2031) 54
Table 27 France Gastrointestinal Endoscopy Revenue by Product Architecture (2021-2031) 55
Table 28 United Kingdom Gastrointestinal Endoscopy Revenue by Care Setting (2021-2031) 56
Table 29 Italy Gastrointestinal Endoscopy Revenue by Product Architecture (2021-2031) 57
Table 30 Asia-Pacific Gastrointestinal Endoscopy Market by Country/Economy (2021-2031) 58
Table 31 Japan Gastrointestinal Endoscopy Domestic Market by Modality (2021-2031) 60
Table 32 China Gastrointestinal Endoscopy Market Value by Healthcare Facility Tier (2021-2031) 62
Table 33 South Korea Gastrointestinal Endoscopy Market by Functional Device Type (2021-2031) 63
Table 34 India Gastrointestinal Endoscopy Market by Clinical Application (2021-2031) 64
Table 35 Taiwan (China) Gastrointestinal Endoscopy Market Size by Architecture (2021-2031) 64
Table 36 Latin America Gastrointestinal Endoscopy Market by Country (2021-2031) 65
Table 37 Brazil Gastrointestinal Endoscopy Market by Modality and Application (2021-2031) 66
Table 38 Mexico Gastrointestinal Endoscopy Market by Modality and Application (2021-2031) 67
Table 39 Middle East and Africa Gastrointestinal Endoscopy Market by Region (2021-2031) 68
Table 40 GCC Gastrointestinal Endoscopy Market by Product Architecture (2021-2031) 69
Table 41 South Africa Gastrointestinal Endoscopy Market by Product Architecture (2021-2031) 69
Table 42 Global Gastrointestinal Endoscopy Market Share Consolidation Metrics (2021-2026) 71
Table 43 Competitive Feature Comparison: Sensor Standard, Articulation, Light Engines, and Reprocessing 72
Table 44 Olympus Corporation Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 77
Table 45 HOYA Corporation Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 80
Table 46 Fujifilm Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 83
Table 47 Medtronic Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 86
Table 48 Shanghai Aohua Photoelectricity Endoscope Co. Ltd. Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 89
Table 49 SonoScape Medical Corp. Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 92
Table 50 Richard Wolf GmbH Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 95
Table 51 IntroMedic Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 98
Table 52 CapsoVision Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 101
Table 53 Jinshan Science & Technology (Group) Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 104
Table 54 AnX Robotics Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 107
Table 55 Insight Medical Solutions Inc Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 110
Table 56 Beijing Huagen Anbang Technology Co. Ltd. Gastrointestinal Endoscopy Revenue, Cost and Gross Margin (2021-2026) 113
Table 57 Consolidated Global Gastrointestinal Endoscopy Forecast Summary (2026-2031) 116
Figure 1 Gastrointestinal Endoscopy Global Value Chain and Production Flow Architecture 7
Figure 2 Endoscope Tip Packaging: Micro-Optics, Distal Cap, and Biopsy Channel Cross-Section 9
Figure 3 Reprocessing Workflow and Infection Risk Transmission Nodes in Flexible Endoscopy 11
Figure 4 Global Value Chain Margin Deconstruction: From Optical Raw Materials to Hospital Billing 13
Figure 5 Global Trade Corridors and Geographic Hub Concentration of Endoscope Exports (2026) 15
Figure 6 Regulatory Clearance Timeframes Across US FDA 510(k), EU MDR, and China NMPA 17
Figure 7 Global Gastrointestinal Endoscopy Market by Architecture: Reusable vs. Disposable (2021-2031) 21
Figure 8 Sensor Cost Disruption: CMOS Miniaturization Curve Driving Disposable Scope Economics 25
Figure 9 Breakdown of Global Gastrointestinal Endoscopy Revenue by Clinical Function (2026) 29
Figure 10 Upper Gastroscope vs. Colonoscope Volume Distribution Across Tier-1 Geographies (2021-2026) 31
Figure 11 Transition Velocity: Reusable Duodenoscopes vs. Single-Use Elevator Caps vs. Fully Single-Use Scopes 34
Figure 12 Magnetically Controlled Capsule Endoscopy (MCCE) System Operational Topology 36
Figure 13 Gastrointestinal Endoscopy Procedural Volume by Downstream Clinical Application (2021-2031) 39
Figure 14 Advanced Resection Market Share: ESD vs. EMR Specialized Capital Systems (2021-2031) 42
Figure 15 ERCP and EUS Diagnostic Yield and Hardware Adoption Curve (2021-2031) 44
Figure 16 North America Gastrointestinal Endoscopy Setting Split: Inpatient Hospital vs. Outpatient ASC (2021-2031) 47
Figure 17 United States Endoscope Replacement Cycles and Installed Base Expansion (2021-2026) 50
Figure 18 European Endoscopy Market Share by Top Five National Economies (2026) 53
Figure 19 Asia-Pacific Gastrointestinal Endoscopy Market Breakdown by Production vs. Consumption Share (2026) 59
Figure 20 China Gastrointestinal Endoscopy Procurement: Domestic Substitution Trajectory (2021-2031) 61
Figure 21 Latin America and MEA Market Access Vulnerability Index (2026) 66
Figure 22 Global Gastrointestinal Endoscopy Competitive Matrix and C4 Concentration Index (2021-2026) 71
Figure 23 Olympus Corporation Gastrointestinal Endoscopy Market Share (2021-2026) 77
Figure 24 HOYA Corporation Gastrointestinal Endoscopy Market Share (2021-2026) 80
Figure 25 Fujifilm Gastrointestinal Endoscopy Market Share (2021-2026) 83
Figure 26 Medtronic Gastrointestinal Endoscopy Market Share (2021-2026) 86
Figure 27 Shanghai Aohua Photoelectricity Endoscope Co. Ltd. Gastrointestinal Endoscopy Market Share (2021-2026) 89
Figure 28 SonoScape Medical Corp. Gastrointestinal Endoscopy Market Share (2021-2026) 92
Figure 29 Richard Wolf GmbH Gastrointestinal Endoscopy Market Share (2021-2026) 95
Figure 30 IntroMedic Gastrointestinal Endoscopy Market Share (2021-2026) 98
Figure 31 CapsoVision Gastrointestinal Endoscopy Market Share (2021-2026) 101
Figure 32 Jinshan Science & Technology (Group) Gastrointestinal Endoscopy Market Share (2021-2026) 104
Figure 33 AnX Robotics Gastrointestinal Endoscopy Market Share (2021-2026) 107
Figure 34 Insight Medical Solutions Inc Gastrointestinal Endoscopy Market Share (2021-2026) 110
Figure 35 Beijing Huagen Anbang Technology Co. Ltd. Gastrointestinal Endoscopy Market Share (2021-2026) 113
Figure 36 Technology Convergence Vector: Robotic Guidance, Hyperspectral Imaging, and Single-Use Platforms 115
Research Methodology
- Market Estimated Methodology:
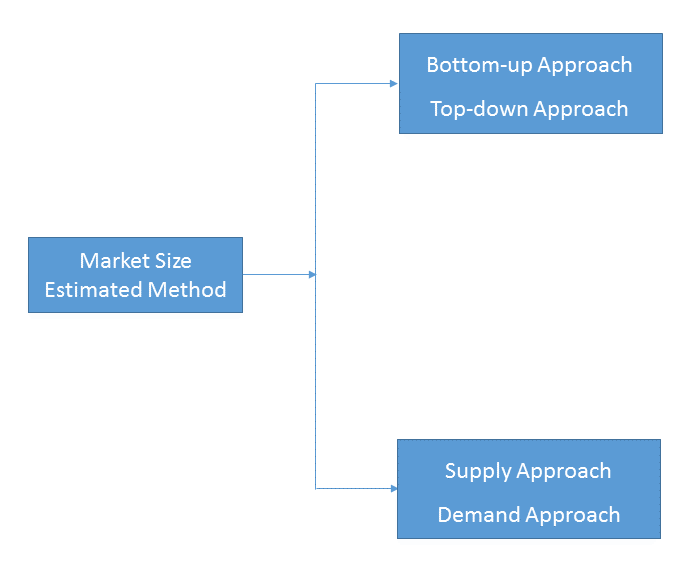
Bottom-up & top-down approach, supply & demand approach are the most important method which is used by HDIN Research to estimate the market size.
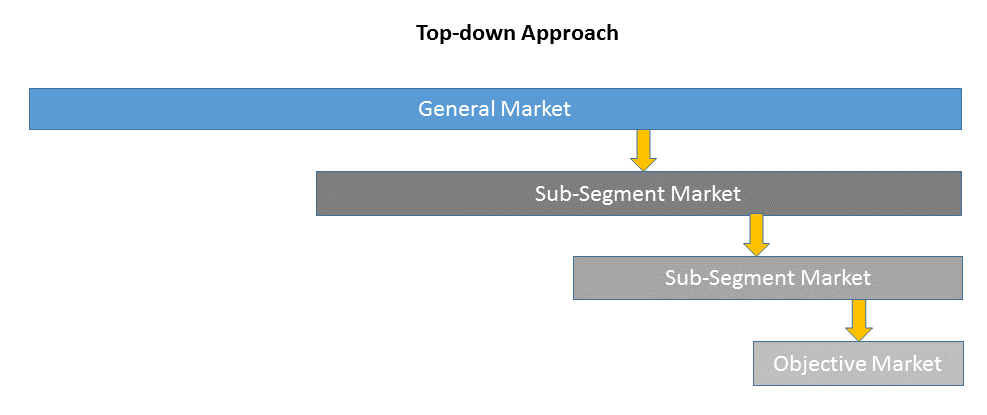
1)Top-down & Bottom-up Approach
Top-down approach uses a general market size figure and determines the percentage that the objective market represents.
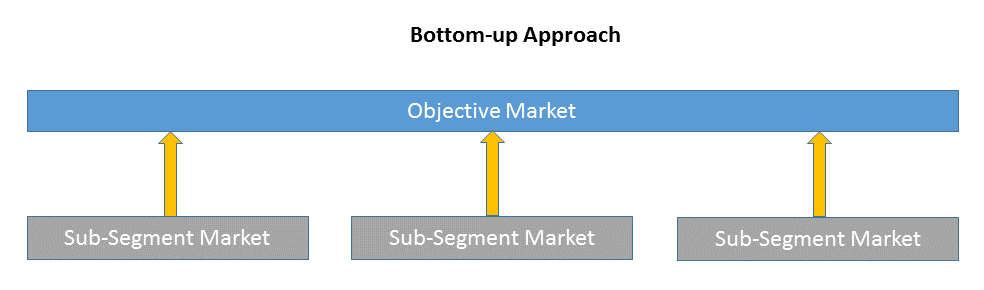
Bottom-up approach size the objective market by collecting the sub-segment information.
2)Supply & Demand Approach
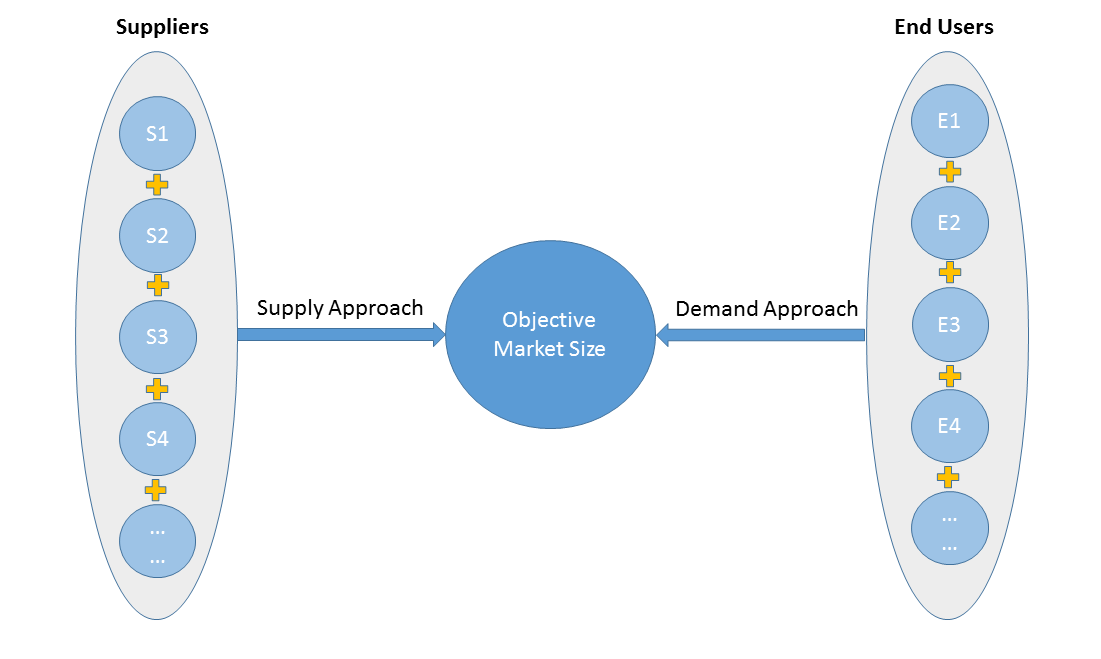
Supply approach is based on assessments of the size of each competitor supplying the objective market.
Demand approach combine end-user data within a market to estimate the objective market size. It is sometimes referred to as bottom-up approach.
- Forecasting Methodology
- Numerous factors impacting the market trend are considered for forecast model:
- New technology and application in the future;
- New project planned/under contraction;
- Global and regional underlying economic growth;
- Threatens of substitute products;
- Industry expert opinion;
- Policy and Society implication.
- Analysis Tools
1)PEST Analysis
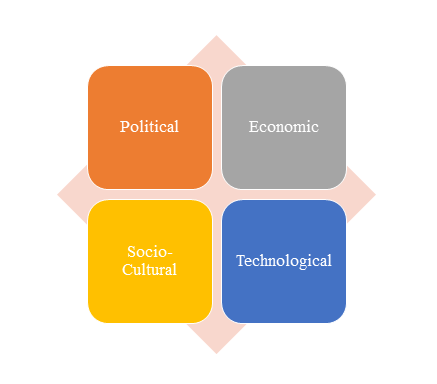
PEST Analysis is a simple and widely used tool that helps our client analyze the Political, Economic, Socio-Cultural, and Technological changes in their business environment.
- Benefits of a PEST analysis:
- It helps you to spot business opportunities, and it gives you advanced warning of significant threats.
- It reveals the direction of change within your business environment. This helps you shape what you’re doing, so that you work with change, rather than against it.
- It helps you avoid starting projects that are likely to fail, for reasons beyond your control.
- It can help you break free of unconscious assumptions when you enter a new country, region, or market; because it helps you develop an objective view of this new environment.
2)Porter’s Five Force Model Analysis
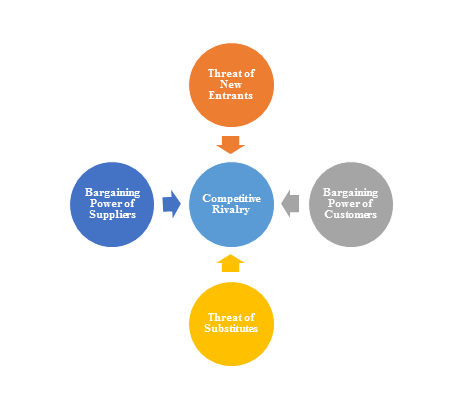
The Porter’s Five Force Model is a tool that can be used to analyze the opportunities and overall competitive advantage. The five forces that can assist in determining the competitive intensity and potential attractiveness within a specific area.
- Threat of New Entrants: Profitable industries that yield high returns will attract new firms.
- Threat of Substitutes: A substitute product uses a different technology to try to solve the same economic need.
- Bargaining Power of Customers: the ability of customers to put the firm under pressure, which also affects the customer's sensitivity to price changes.
- Bargaining Power of Suppliers: Suppliers of raw materials, components, labor, and services (such as expertise) to the firm can be a source of power over the firm when there are few substitutes.
- Competitive Rivalry: For most industries the intensity of competitive rivalry is the major determinant of the competitiveness of the industry.
3)Value Chain Analysis
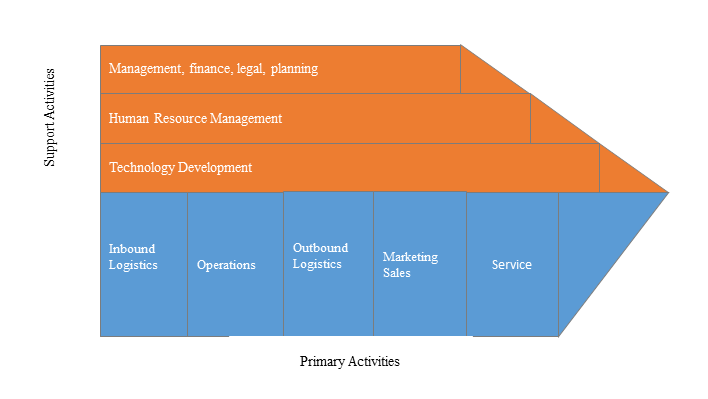
Value chain analysis is a tool to identify activities, within and around the firm and relating these activities to an assessment of competitive strength. Value chain can be analyzed by primary activities and supportive activities. Primary activities include: inbound logistics, operations, outbound logistics, marketing & sales, service. Support activities include: technology development, human resource management, management, finance, legal, planning.
4)SWOT Analysis
SWOT analysis is a tool used to evaluate a company's competitive position by identifying its strengths, weaknesses, opportunities and threats. The strengths and weakness is the inner factor; the opportunities and threats are the external factor. By analyzing the inner and external factors, the analysis can provide the detail information of the position of a player and the characteristics of the industry.
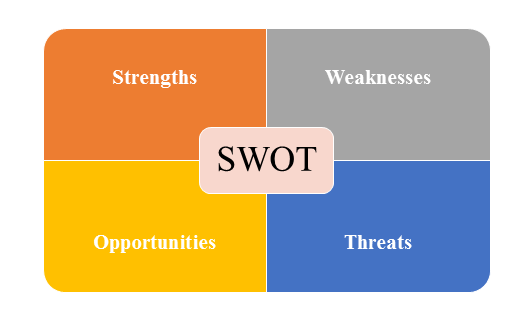
- Strengths describe what the player excels at and separates it from the competition
- Weaknesses stop the player from performing at its optimum level.
- Opportunities refer to favorable external factors that the player can use to give it a competitive advantage.
- Threats refer to factors that have the potential to harm the player.
- Data Sources
| Primary Sources | Secondary Sources |
|---|---|
| Face to face/Phone Interviews with market participants, such as: Manufactures; Distributors; End-users; Experts. Online Survey |
Government/International Organization Data: Annual Report/Presentation/Fact Book Internet Source Information Industry Association Data Free/Purchased Database Market Research Report Book/Journal/News |